Global Cause


Dr Frenk Smrekar
CEO, JAFRAL
When antibiotics stop working, doctors need alternatives. Phage therapy, a century-old idea, is regaining ground as a precise, targeted treatment.
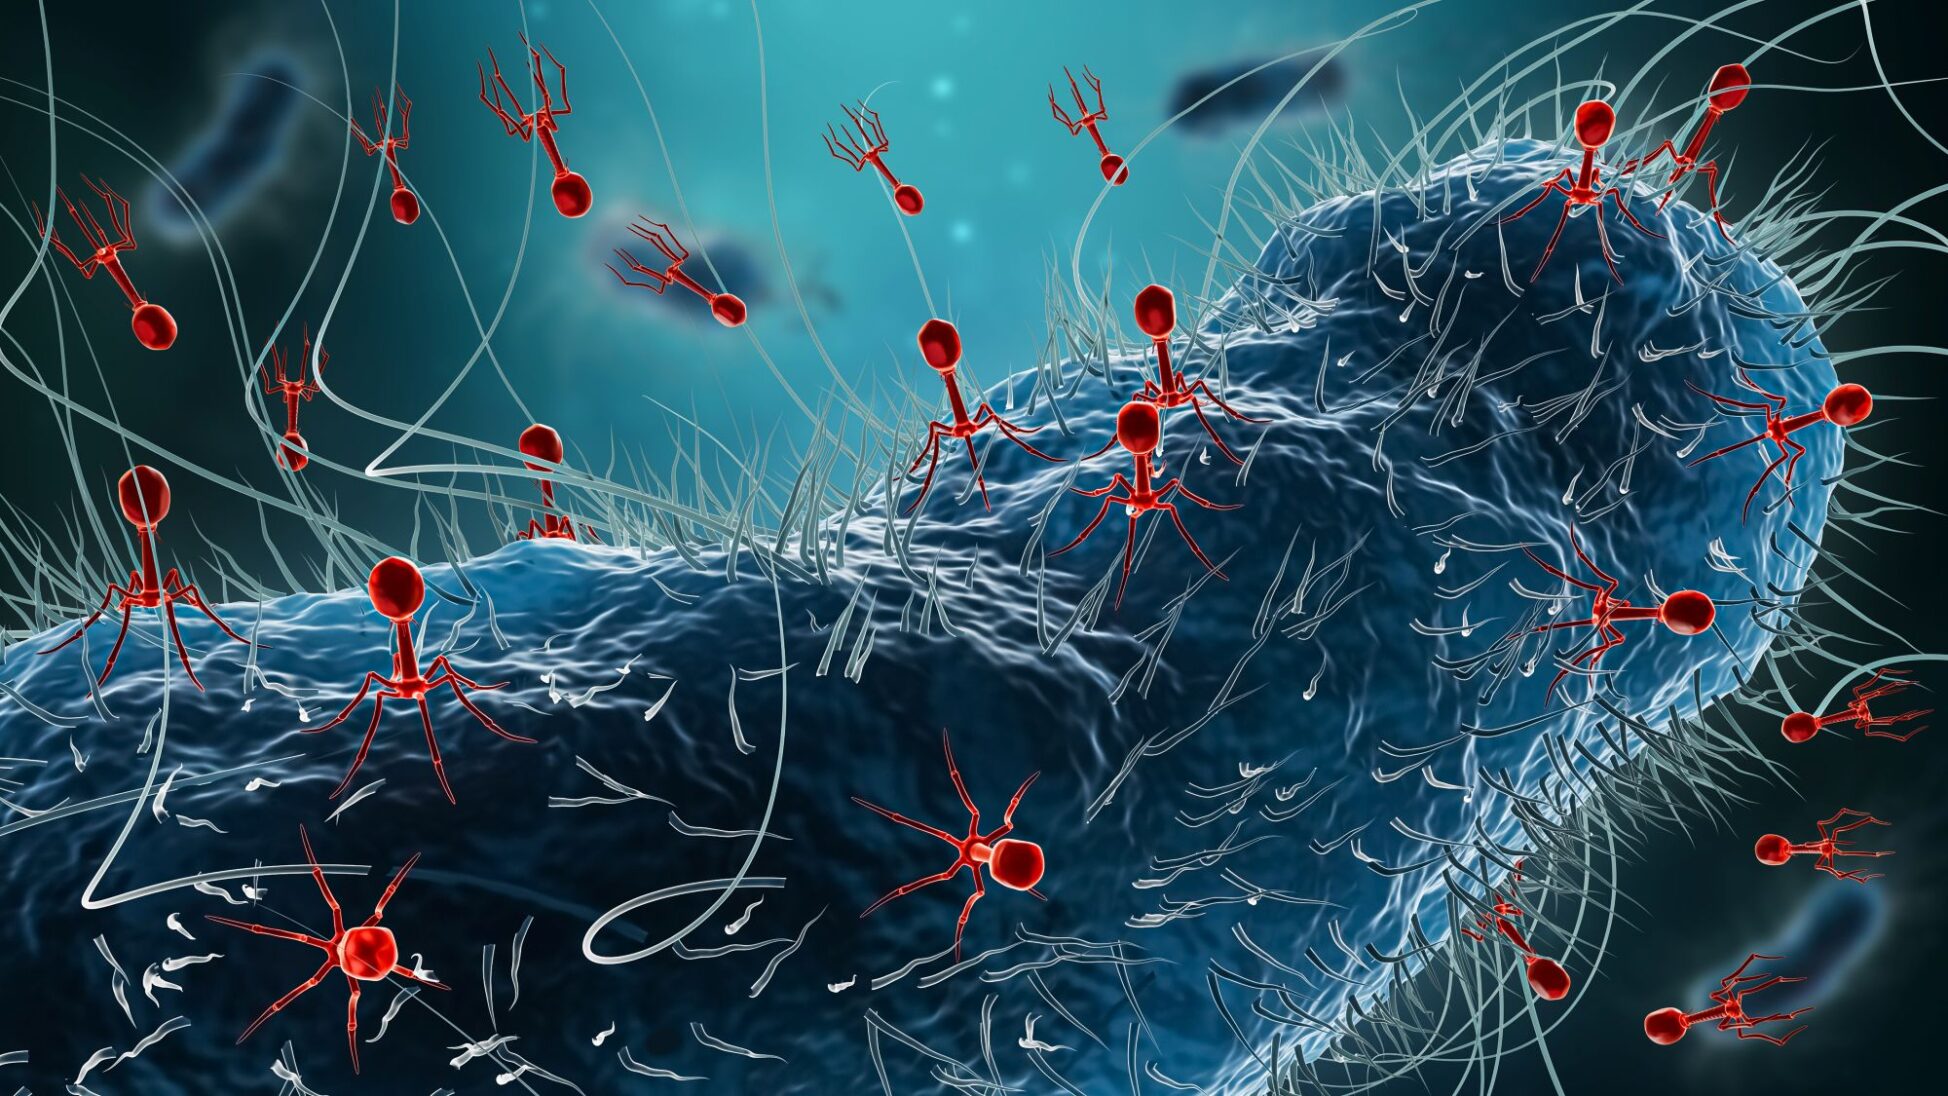
Bacteriophages, or ‘phages’, are natural viruses that infect and kill bacteria. Each phage targets a specific bacterial strain while leaving everything else, including the patient’s microbiome, untouched.
Phages work where antibiotics can’t
“Antibiotics and phages attack bacteria in completely different ways,” explains Dr Frenk Smrekar, CEO of Slovenian (EU) company JAFRAL, the world’s largest dedicated bacteriophage contract manufacturer. “Bacteria that have become resistant to antibiotics have no built-in defence against a phage.
“That’s why even ‘superbugs’ that no antibiotic can touch are usually still vulnerable to the right phage — and the two treatments can be used together, often reinforcing each other.” Moreover, phages can reach into biofilms (protective layers on wounds, implants or catheters) that antibiotics struggle to get through.
The manufacturing side is ready; we have GMP capacity and phage banks in place
Matched to the patient
Interest has revived as resistance grows, and as advances in sequencing and biologics production mean a phage can be matched to an infection in days, not months. “We screen the patient’s bacterial isolate against ready-made phages,” says Dr Smrekar. “If one is active, we can deliver within two to three days; if not, we produce a new phage from scratch within two to three weeks.” JAFRAL was the first company worldwide to list its GMP products (JAFPA-001, etc.) in the EudraGMDP database as an inspected active substance. Additionally, JAFRAL manufactured Clinical Trial Products for 14 clinical trials.
From personalised to routine care
No phage product yet has full marketing authorisation in the EU or US; patients are treated with individually prepared phages. “Regulators have been cooperative and proactive in recent years,” says Dr Smrekar. “The manufacturing side is ready; we have GMP capacity and phage banks in place. What’s needed now is more clinical trials and real-world evidence, and we’re contributing to them.”
He expects registered phage products to become a routine in hospital infection pathways, backed by personalised solutions where broad-spectrum cocktails don’t suffice. “Once the technology is well tested, it makes sense to use phages earlier, alongside antibiotics, and relieve the burden on antibiotic use,” he concludes.